 SehatSphere.com
GERD and Silent Reflux: Why Your Acidity Isn’t What You Think It Is
Good GERD and silent reflux management starts with a fact most people never hear: India carries the highest number of GERD cases of any country on earth — and a huge share of it never shows up as heartburn at all. If you’ve been coughing, clearing your throat, or losing your voice for months with every doctor checking your lungs instead of your stomach, this guide is for you.

Key takeaways:
- India has an estimated 194 million people living with GERD — more than any other country — yet only about a third take medication for it regularly.
- “Silent reflux” (LPR) often skips heartburn entirely and shows up as hoarseness, throat-clearing, or a chronic cough — which is why it gets misdiagnosed as asthma or allergies for years.
- A handful of everyday medications, including some blood pressure drugs, physically relax the valve that’s supposed to keep acid down.
- Stopping acid medication suddenly after long-term use can trigger a rebound that feels worse than the original problem — it isn’t your GERD coming back.
What I Actually See at the Counter
People walk in clutching an antacid strip or a pantoprazole packet, looking genuinely tired, saying the same thing almost word for word: “I take it every day, but the moment I stop, it’s back.” That single sentence tells me more than most lab reports — it usually means nobody has explained why the medicine works, only that it does. It’s the same gap we’ve written about across our Complete Guide to Medicine Safety — medicines that work brilliantly when the “why” is missing from the conversation.
The Valve That’s Supposed to Stop This
At the junction where your food pipe meets your stomach sits a ring of muscle called the Lower Esophageal Sphincter (LES). It stays shut most of the time, opening only to let food down or to release a burp. Reflux happens when this valve relaxes at the wrong moments — a transient LES relaxation — letting acid and digestive enzymes splash back up into a food pipe that has no protective lining against them.
What makes this valve misbehave is rarely one single thing, and understanding it is central to genuine GERD and silent reflux management. A hiatal hernia (where part of the stomach pushes up through the diaphragm), extra weight pressing on the abdomen, chronic stress (the same stress-hormone cascade we cover in our anger and blood pressure guide also slows digestion and loosens this valve), and specific foods and drinks that chemically relax the LES muscle — caffeine, peppermint, chocolate, alcohol — all make the same mechanical failure more likely.

This is the part of the job that rarely gets seen — cross-checking a patient’s actual medication list against what’s known to affect this exact valve, before just handing over another antacid.
Silent Reflux: The Epidemic Doctors Miss
Most people assume reflux always means heartburn. Laryngopharyngeal reflux (LPR) — “silent reflux” — breaks that assumption completely. Instead of stopping at the food pipe, acid and airborne pepsin travel further up, past a second valve, into the throat and voice box. Because the tissue there has almost no acid tolerance, even small amounts cause outsized irritation — without ever producing the burning chest sensation people associate with reflux.
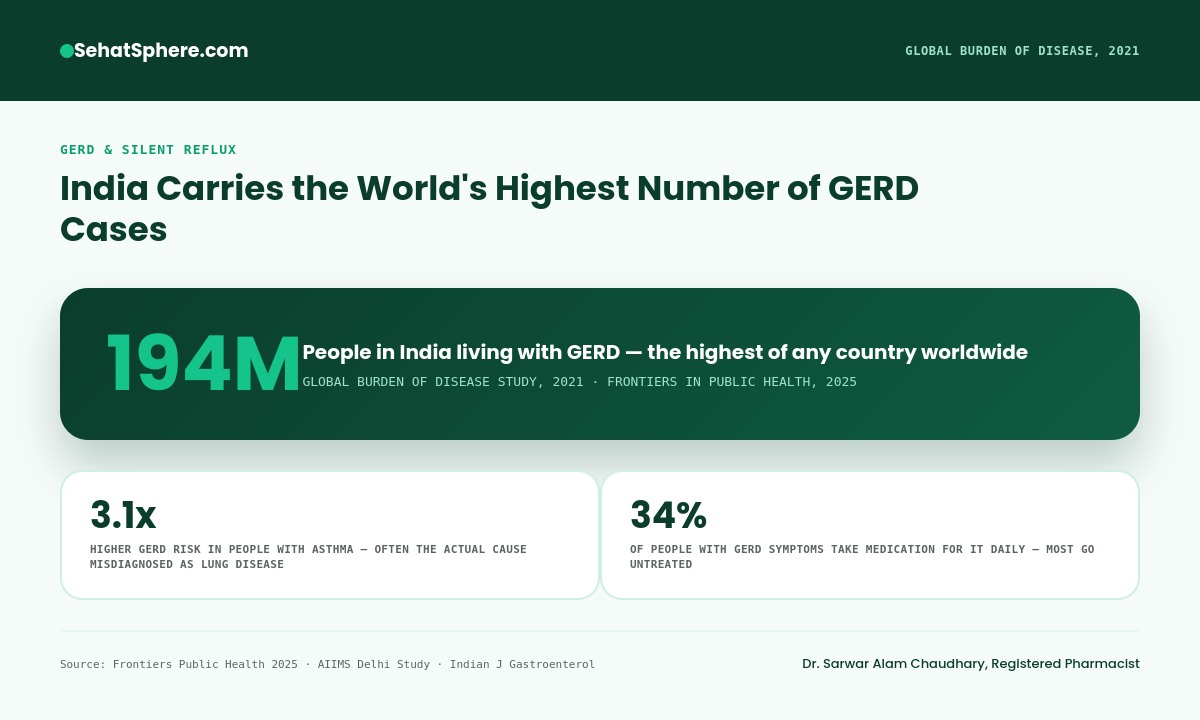
This is exactly why LPR gets missed for years: chronic throat-clearing looks like a lingering cold, a raspy morning voice looks like overuse, and a dry cough looks like asthma. One real, specific number makes this last point concrete: people with asthma carry roughly 3.1 times higher odds of having undiagnosed GERD feeding their symptoms — a connection a chest X-ray will never show.

- Chronic throat-clearing — a persistent tickle or urge to clear mucus through the day
- Globus sensation — a constant feeling of a lump or pill stuck in the throat
- Hoarseness and voice fatigue — often worst first thing in the morning
- A dry cough with no chest congestion to explain it
Nighttime reflux specifically disrupts sleep architecture without always waking you up fully — if you’re also dealing with unexplained daytime exhaustion, our guide on why you’re still tired after 8 hours of sleep covers this exact overlap.
What To Read Next
- Pantoprazole Side Effects: Long-term risks and how to safely stop, if you’re on a PPI for this.
- Magnesium and Your Medications: Why long-term acid suppression is specifically flagged for magnesium loss.
- Vitamin B12 Deficiency: Another nutrient long-term acid suppression can quietly deplete.
- Complete Guide to Blood Pressure: If a calcium channel blocker is part of your medication list.
- Nutrient Deficiency Symptom Finder: Free 2-minute check if fatigue has crept in alongside reflux.
Medications That Quietly Trigger Reflux
This is the detail almost no reflux article mentions, and it’s genuinely useful if you’re managing more than one condition at once. Several common, everyday medications relax the same LES valve described above — not as a rare side effect, but as a documented, mechanism-level effect of the drug class itself.
| Medication Class | Example | Why It Matters |
|---|---|---|
| Calcium channel blockers | Amlodipine | Relaxes smooth muscle generally, including the LES |
| Benzodiazepines | Alprazolam, diazepam | Reduces LES muscle tone as part of its calming effect |
| Beta-2 agonists | Salbutamol inhalers | Relaxes airway and esophageal smooth muscle |
| Nitrates | Isosorbide | Vasodilating effect extends to the LES muscle |
None of this means these medications should be stopped — they’re doing an important job for whatever they were prescribed for. It means that if you’re on any of these and also managing reflux, that’s a genuine connection worth mentioning to your doctor, not two unrelated problems. If your blood pressure readings have also been inconsistent, it’s worth knowing whether your specific BP medication is a calcium channel blocker — our normal blood pressure by age guide and BP medicine timing guide cover the bigger picture around these same medications. If you’re on multiple prescriptions at once, our free Integrative Interaction Checker is worth running your full list through.
Treatment: What Actually Helps With GERD and Silent Reflux Management
Lasting relief usually needs all three of these working together, not just one:
| Category | What It Does |
|---|---|
| Antacids & alginates | Neutralize acid fast or form a physical foam “raft” on top of stomach contents |
| H2 blockers (famotidine) | Milder, longer-acting acid reduction — often used as a step-down from a PPI |
| PPIs (pantoprazole, omeprazole) | Near-complete acid suppression for healing — the strongest option, not the first-line one |

The lifestyle side matters just as much as the pill, and it’s genuinely evidence-based rather than folk wisdom: a 3-hour gap between your last meal and lying down, raising the head of the bed by 6–8 inches (not just stacking pillows, which bends the body at the wrong point), sleeping on your left side specifically, and smaller, more frequent meals instead of large ones that stretch the stomach and force the valve open.
Two “natural remedy” habits deserve a specific word of caution rather than blanket approval. Apple cider vinegar is often recommended online for reflux on the theory that low stomach acid is the real problem — our full ACV guide covers why this logic doesn’t hold up for most people with genuine GERD, and why adding more acid to an already-irritated esophagus can make things worse, not better. Ashwagandha, often taken for stress, has its own interaction profile worth checking before adding it to an already-full medication list. And if your reflux is worse on days you’ve had a proffee or an energy drink, our proffee guide explains exactly why — concentrated caffeine is one of the most reliable LES-relaxing triggers there is.
The Rebound Trap When You Stop
Long-term PPI use trains your stomach to produce more acid-making machinery to compensate for the suppression — stop suddenly, and that machinery floods your system with more acid than you had before you ever started. This is rebound acid hypersecretion, and it’s the single biggest reason people feel “stuck” on these medications indefinitely, convinced their original problem has gotten worse.
Our full pantoprazole guide covers the exact tapering protocol and the real study data behind it — in one controlled trial, 44% of genuinely healthy volunteers had acid symptoms after stopping an 8-week PPI course, compared to 15% on placebo. That gap is the rebound effect, not disease progression. Long-term PPI use also carries its own separate risks worth knowing about — magnesium deficiency chief among them, plus B12 and fracture risk over years of continuous use. If you’re also managing cholesterol alongside reflux, our statins guide covers a similar pattern of symptoms that get blamed on the wrong medication more often than people realize.
A Real Case From the Counter
A 39-year-old software architect came in with months of morning hoarseness, a nighttime cough, and a constant lump-in-throat feeling. His routine: a double espresso late at night while working, followed by peppermint gum before bed, then lying flat almost immediately. Both caffeine and peppermint directly relax the LES — and lying flat right after gave acid vapor a clear path to his throat. Cutting the late-night coffee and mint, adding a strict 3-hour pre-bed gap, and a short course of alginate therapy resolved it within three weeks — no new prescription required.
He also happened to be a gym regular on creatine, and asked if that played any role — it doesn’t, directly, though our creatine and blood test guide is worth reading if you’re on it and ever get an unrelated lab flag. For a broader sense of how daily habits like this add up, our free Biological Longevity Audit is a reasonable starting point.
When It’s Not Just Reflux
Unexplained weight loss, difficulty swallowing, vomiting blood, or chest pain that radiates to your arm or jaw are not typical reflux symptoms — they need direct medical evaluation, not a stronger antacid. Left untreated for years, chronic acid exposure can also lead to esophageal narrowing or Barrett’s esophagus, a precancerous tissue change — rare, but the reason persistent symptoms deserve an actual diagnosis rather than indefinite self-medication. Chronic, low-grade blood loss from an irritated esophagus can also show up as unexplained fatigue long before it shows up as anything dramatic — our iron deficiency anemia guide and the free Blood Report Decoder are worth a look if a routine blood test ever flags this alongside your reflux.
Which Pattern Is Yours?
Tick anything that applies to you, and see what it suggests.
Frequently Asked Questions About GERD and Silent Reflux Management
What is the main cause of GERD and acid reflux?
GERD is primarily caused by the Lower Esophageal Sphincter relaxing at the wrong times, allowing stomach acid to flow back into the esophagus. Diet, weight, and certain medications all influence how often this happens.
How is silent reflux (LPR) different from regular GERD?
LPR pushes acid further up into the throat and voice box, causing hoarseness, throat-clearing, and cough rather than the classic burning chest pain of typical GERD. Many people with LPR never experience heartburn at all.
Why do reflux symptoms come back worse after stopping medication?
Long-term acid suppression causes your stomach to compensate by increasing acid-producing capacity. Stopping abruptly triggers rebound acid hypersecretion, which feels like the original condition worsening but is actually a temporary withdrawal effect.
Can blood pressure medication cause acid reflux?
Yes, specifically calcium channel blockers like amlodipine, which relax smooth muscle throughout the body, including the esophageal valve responsible for keeping acid down.
Do coffee and mint really make reflux worse?
Yes, both chemically relax the Lower Esophageal Sphincter, making it easier for stomach contents to move upward, especially when consumed close to bedtime.
What lifestyle changes help prevent nighttime reflux?
A 3-hour gap between your last meal and lying down, elevating the head of the bed by 6-8 inches, and sleeping on your left side are the most evidence-supported changes.
Can silent reflux be mistaken for asthma?
Yes, frequently. People with asthma have roughly 3 times higher odds of undiagnosed GERD, and a chronic dry cough from LPR is often treated as a respiratory issue for years before reflux is considered.
What are the long-term risks of untreated GERD?
Chronic, uncontrolled acid exposure can lead to esophageal strictures, ulcers, and Barrett’s esophagus, a precancerous change in the esophageal lining.
When should I see a doctor instead of managing reflux myself?
Seek prompt evaluation for unexplained weight loss, difficulty swallowing, vomiting blood, or chest pain radiating to the arm or jaw – these need direct medical assessment.
How common is GERD in India?
Estimates vary by study, but India is estimated to carry around 194 million cases, the highest number of any country, with population studies typically finding somewhere between 8% and 30% prevalence depending on region and methodology.
The Bottom Line on GERD and Silent Reflux Management
Reflux isn’t really about too much acid — it’s about a valve that isn’t staying shut when it should. Silent reflux takes that same mechanism and sends it somewhere you’d never think to blame, which is exactly why it goes undiagnosed for years. Good GERD and silent reflux management means treating both patterns as the same underlying problem, not two separate diseases. A handful of everyday medications, your evening coffee habit, and how you sleep all genuinely move the needle here — more than most people realize, and more than another round of antacids ever will.
- American College of Gastroenterology. Clinical Guideline for GERD. gi.org
- Global, regional, and national burden of gastroesophageal reflux disease (1990-2021). Frontiers in Public Health, 2025.
- Cleveland Clinic. Laryngopharyngeal Reflux (LPR). clevelandclinic.org