 SehatSphere.com
Iron Deficiency Anemia: 7 Warning Signs, 3 Hidden Stages, and the Overdose Risk Nobody Mentions
- Iron deficiency anemia is India’s single most common nutrient gap, and it develops through
three silent stages — your storage iron (ferritin) can be running low for months before hemoglobin, the number on a standard blood test, ever drops. - Fatigue, pale skin, breathlessness, cold hands, brittle nails, restless legs, and pica (craving non-food items) are the 7 signs worth watching — most people notice several long before connecting them to iron.
- Restless legs can appear from low iron even without full anemia — research points to a serum ferritin threshold of 75 ng/mL or below for a trial of oral iron, tied to a real brain-dopamine mechanism, not just a folk remedy.
- Iron is a leading cause of fatal accidental poisoning in children under 6, per the NIH’s own consumer guidance — a fact almost no iron-deficiency article actually mentions, and the single most important safety point in this one.
- Iron supplements block absorption of levothyroxine (thyroid medicine) and certain antibiotics if taken too close together — a 4-hour and 2–6 hour spacing rule respectively, both from real drug-interaction data, not folklore.
- Pregnant women need 27 mg/day — roughly 1.5× the non-pregnant requirement — which is why WHO recommends routine iron and folic acid supplementation as part of standard antenatal care.

Iron deficiency anemia is India’s single most common nutrient deficiency, and yet it’s routinely mistaken for ordinary tiredness, a busy schedule, or “just needing more sleep.” Part of the reason is that iron deficiency doesn’t arrive all at once — it moves through three distinct, mostly silent stages before it ever becomes the anemia a standard blood test would catch. This guide covers the 7 real warning signs, the 3 stages nobody talks about, how hemoglobin and ferritin actually differ as tests, the surprising restless-legs and pregnancy connections, and — a section almost every other guide skips — the real overdose risk that makes “just take more iron” genuinely bad advice without a confirmed deficiency first.
1. Why Iron Deficiency Anemia Gets Missed So Often
Iron deficiency develops gradually, in stages (the next section walks through exactly how). Your body first draws down stored iron reserves before hemoglobin — the oxygen-carrying protein in blood — actually starts to drop. This means someone can be meaningfully iron-depleted for months before a standard checkup, which usually only measures hemoglobin, would catch anything unusual.
Fatigue is the single most common sign, and also the least specific one — nearly everyone attributes tiredness to stress, poor sleep, or a demanding week long before considering a nutrient deficiency. It usually takes several signs appearing together, not just one, before iron deficiency becomes a reasonable thing to actually test for.
This gradual onset also means the person experiencing it often adapts without realizing it — quietly avoiding stairs, sitting down more often, or simply accepting a lower baseline energy level as normal, which delays recognition even further.
2. The 3 Hidden Stages of Iron Deficiency
This is the part most patient-facing guides skip entirely, and it’s the reason a “normal” blood test can still miss a real, developing problem. Iron deficiency isn’t a single event — it’s a progression through three distinct physiological stages, and only the last one is technically “anemia.”
Stage 1 — Iron Depletion
Your body’s iron stores, measured by ferritin, start dropping. At this point your bone marrow can still make perfectly normal red blood cells by pulling from reserves, so hemoglobin stays completely normal and you likely feel nothing at all. Ferritin is the only marker that has moved.
Stage 2 — Iron-Deficient Erythropoiesis
Reserves are now low enough that red blood cell production itself starts to be constrained. Transferrin saturation (the percentage of your iron-transport protein that’s actually carrying iron) drops, and the marrow starts producing red cells that are subtly smaller and less iron-rich than normal — but hemoglobin can still sit within the “normal” reference range on a routine report, especially if the lab’s cutoff is lenient. Vague symptoms like mild fatigue often start here, before any test flags it clearly.
Stage 3 — Iron-Deficiency Anemia
Compensation finally fails. Hemoglobin drops below the normal threshold, red blood cells become visibly smaller on a blood film (a low MCV, or mean corpuscular volume — this is what “microcytic anemia” means), and this is the point where most of the 7 signs in the next section become impossible to ignore.
If your hemoglobin came back “normal” but you still have several of the 7 signs below, you may simply be in Stage 1 or 2 rather than deficiency-free. Asking specifically for a ferritin test, not just a routine hemoglobin check, is what actually catches this earlier — a point covered in more depth in the hemoglobin-vs-ferritin section further down.

Ferritin moves first, transferrin saturation second, hemoglobin last — which is exactly why a “normal” hemoglobin doesn’t rule out an iron problem already in progress.
🩸 Already Have Your Numbers?
Our Blood Report Decoder reads hemoglobin, ferritin, MCV, transferrin saturation, and 17 other common markers together, automatically flagging exactly which stage a result pattern points to — faster than checking one number at a time.
3. The 7 Warning Signs of Iron Deficiency Anemia
These seven signs are the ones most consistently documented in clinical literature, and they’re mostly Stage 3 signs — the point where compensation has run out. Most people notice a few of these long before ever connecting them to iron.
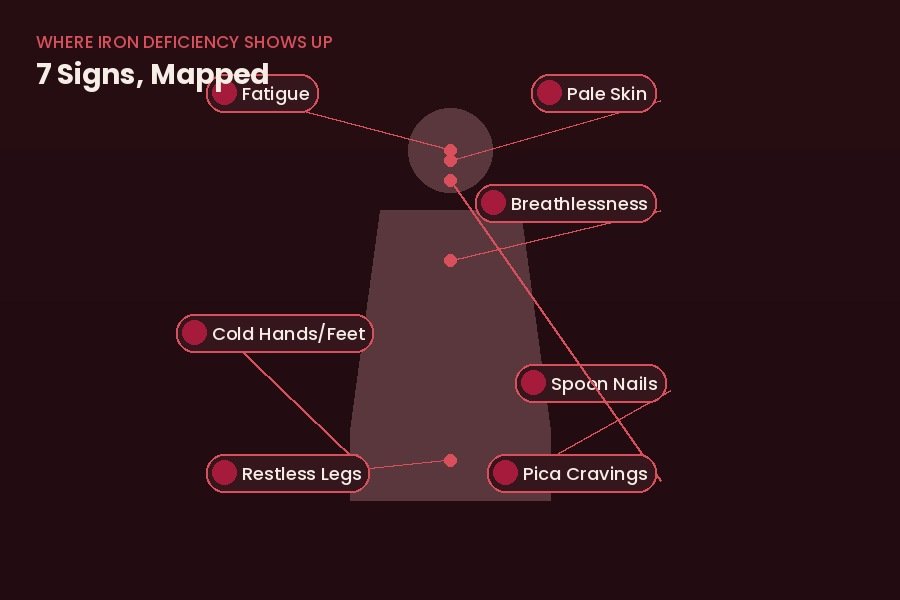
1. Persistent Fatigue
Without enough iron, your body can’t make enough hemoglobin to carry oxygen efficiently to your tissues, leaving you feeling drained regardless of how much you sleep. This fatigue tends to feel heavier and more constant than ordinary tiredness, though it’s rarely recognized as different until it’s pointed out directly. A useful distinction: ordinary tiredness usually improves noticeably after a good night’s sleep, while iron-deficiency fatigue tends to persist regardless of rest.
2. Pale Skin
Hemoglobin is what gives blood, and by extension skin, its healthy color. A noticeably pale complexion, pale inner eyelids, or pale nail beds are classic, visible signs of anemia — often something family members notice before the person experiencing it does. Checking the inner lower eyelid specifically is a simple, commonly taught trick — a healthy pink-red color versus a pale, washed-out appearance can be a useful visual clue even before any blood test.
3. Shortness of Breath
When less oxygen reaches your muscles and tissues, ordinary activities — climbing stairs, brisk walking, light exercise — can leave you noticeably more breathless than they used to. This is frequently mistaken for being out of shape rather than a blood-oxygen issue. A genuine change from your own baseline — if stairs that used to be easy suddenly feel difficult over a period of weeks — is more meaningful than the absolute fitness level.
4. Cold Hands and Feet
Reduced oxygen delivery affects circulation to your extremities first, which is why persistently cold hands and feet, even in warm conditions, is a recognized sign worth paying attention to alongside the others on this list. This is genuinely easy to dismiss, especially in people who already run cold naturally, which is part of why it works better as supporting evidence alongside other signs rather than a standalone red flag.
5. Brittle or Spoon-Shaped Nails
This is one of the more distinctive signs on this list. Nails that become unusually brittle, thin, or develop a concave, spoon-like shape — a condition called koilonychia — are specifically associated with more significant, longer-standing iron deficiency rather than a mild, recent one. Because this sign typically appears later than fatigue or paleness, its presence generally suggests the deficiency has been present for a meaningful stretch of time.
6. Restless Legs
An uncomfortable urge to move your legs, particularly at night, has a well-documented link to low iron stores — specific enough that iron levels are one of the first things checked when restless legs syndrome is evaluated. This connection runs deeper than most guides mention, and gets its own dedicated section further down.
7. Unusual Cravings (Pica)
Craving and sometimes eating non-food substances — ice, dirt, chalk, or raw starch — is a distinctive, well-documented sign specifically linked to iron deficiency. It’s genuinely one of the more surprising connections on this list, and also gets its own dedicated section further down.
“If my hemoglobin is normal, I don’t have an iron problem.”
Ferritin, your iron storage marker, drops in Stage 1 — well before hemoglobin moves in Stage 3. A normal hemoglobin only rules out full-blown anemia, not an iron problem already underway.
4. Check Your Iron Deficiency Risk
Tick any symptoms that apply to you right now. This is a rough self-check, not a diagnosis.
This tool is for general awareness only and can’t replace a blood test or a doctor’s evaluation.
5. Who’s Most Likely to Have Iron Deficiency Anemia
Women of reproductive age carry the highest risk of any group, since menstrual blood loss removes meaningful iron every single month — heavier periods mean proportionally higher risk. This is also directly reflected in the RDA: the NIH’s Office of Dietary Supplements sets iron requirements at 8 mg/day for adult men but 18 mg/day for women aged 19–50 — more than double, purely to offset monthly losses.
Pregnant women have substantially increased iron needs — 27 mg/day, covered in its own section further down — to support both increased blood volume and fetal development, making this one of the most consistently monitored groups for iron status.
Vegetarians and vegans absorb non-heme iron, the form found in plant foods, considerably less efficiently than the heme iron found in meat — the NIH notes vegetarians may need almost twice as much dietary iron as non-vegetarians to reach the same absorbed amount, making dietary planning more important for this group specifically.
Frequent blood donors and endurance athletes both lose iron through mechanisms unrelated to diet — donation directly, and endurance training through a combination of increased red blood cell turnover and mild gastrointestinal blood loss.
People with digestive conditions such as celiac disease, Crohn’s disease, or anyone who has had gastric bypass surgery often absorb iron poorly regardless of intake. People on long-term acid-suppressing medication belong in this group too — stomach acid is what converts dietary iron into an absorbable form, so chronic PPI or antacid use quietly reduces iron absorption the same way it affects magnesium and B12, a mechanism our chronic antacids and mineral malabsorption guide covers in full cellular detail.
Children and adolescents, particularly during rapid growth spurts, have proportionally higher iron requirements relative to their size, and teenage girls specifically combine this growth demand with the onset of menstrual blood loss — a combination worth being aware of for parents.
6. Hemoglobin vs Ferritin: Why Both Tests Matter
These two tests measure genuinely different things, and confusing them is one of the most common reasons iron deficiency gets missed on a routine checkup — it’s the direct clinical consequence of the 3-stage progression covered earlier.
Hemoglobin measures the oxygen-carrying protein currently circulating in your blood right now. It’s part of nearly every standard blood test, but per the staging above, it only drops once deficiency has progressed all the way to Stage 3.
Ferritin measures your body’s stored iron reserves — essentially your iron savings account, and the Stage 1 marker. Ferritin typically falls well before hemoglobin does, making it a meaningfully earlier and more sensitive indicator of an iron problem developing.
This is exactly why asking for ferritin specifically, rather than assuming a normal hemoglobin rules out an iron issue, makes a genuine difference in catching a deficiency before it progresses to full-blown anemia with all seven signs in play.
It’s also worth knowing that ferritin can be temporarily elevated by inflammation or infection, independent of actual iron status, which is why testing during or right after being sick can occasionally give a misleadingly reassuring result. Testing during a period of normal health gives a clearer picture.
For a broader clinical reference on iron’s role and deficiency, the National Institutes of Health’s consumer fact sheet on iron is a solid, freely available resource.
7. Iron Deficiency vs B12 Deficiency Anemia: Telling Them Apart
Both iron and B12 deficiency can cause anemia, but they work through entirely different mechanisms — and mixing them up leads to the wrong fix entirely. MCV, a measure of average red blood cell size, is the key differentiator.
Iron deficiency typically produces smaller-than-normal red blood cells (Stage 3’s microcytic pattern), since there isn’t enough iron to properly build each cell’s oxygen-carrying capacity. B12 deficiency, covered in depth in our vitamin B12 guide, produces the opposite pattern — larger, less efficient cells, since B12 is needed for normal cell division.
| Marker | Iron Deficiency | B12 Deficiency |
|---|---|---|
| MCV (cell size) | Low (small cells) | High (large cells) |
| Ferritin | Low | Usually normal |
| Common trigger | Blood loss, poor absorption | Vegetarian diet, absorption issues |
Both deficiencies can technically coexist in the same person, particularly in vegetarians, which is exactly the kind of combined pattern our Blood Report Decoder is built to flag automatically rather than requiring you to cross-reference each marker manually. If you’d rather work through your full symptom picture across all ten commonly-missed nutrients at once, our nutrient deficiency finder tool scores iron, B12, and eight others side by side.
This distinction matters clinically because the fix is completely different for each — iron supplementation won’t correct a B12 deficiency, and B12 supplementation won’t correct an iron one, regardless of how similar the fatigue and paleness might feel from the outside.
8. The Restless Legs Connection: What’s Actually Happening in Your Brain
This is the sign from the list above that surprises people most, and it deserves more than a passing mention, because the mechanism is genuinely interesting and clinically actionable.
Restless legs syndrome (RLS) isn’t just “linked” to iron deficiency in a vague sense — there’s a specific, studied brain mechanism behind it. Research reviewed in a 2021 Mayo Clinic Proceedings management algorithm shows that people with RLS have measurably lower iron stores in specific regions of the brain, and this correlates with a
Here’s the clinically important part: this can happen even when you are not anemic at all. Brain iron and blood iron aren’t the same pool, and the updated management algorithm specifically recommends starting a trial of oral iron when serum ferritin is 75 ng/mL or below and transferrin saturation is under 45% — a threshold well above what most labs flag as “deficient,” which is exactly why RLS from low-normal iron so often gets dismissed as unrelated to nutrition.
If you have restless legs at night and your last ferritin result was anywhere close to 75 ng/mL or below — even if a lab flagged it as “within range” — that’s worth raising specifically with a doctor as a possible iron-responsive cause, rather than accepting restless legs as something to just live with.
Pregnancy and restless legs are also connected through this same pathway — the increased iron demand of pregnancy (see the pregnancy section below) can be enough to trigger RLS symptoms in some women who never had them before, and these often resolve after delivery as iron status normalizes.
9. The Pica Phenomenon: Iron’s Strangest Symptom
Of all seven signs covered in this guide, pica is the one people are least likely to connect to iron on their own. Pica is a craving for and sometimes consumption of non-food substances — ice is the most common (sometimes called pagophagia specifically), though dirt, chalk, paper, and raw starch have all been documented.
The exact biological mechanism behind pica isn’t fully understood, but its connection to iron deficiency is well-documented and repeatedly observed clinically. What makes this symptom particularly useful diagnostically is that it often resolves within days to weeks of starting iron correction, well before other signs like fatigue fully improve — making it one of the more satisfying signs to track during treatment.
Pica during pregnancy specifically deserves a mention, since pregnancy is already a higher-risk period for iron deficiency, and cravings that might otherwise be brushed off as an unusual pregnancy craving are worth mentioning to a doctor rather than assumed to be harmless.
10. Iron Deficiency Anemia in Pregnancy
Pregnancy is one of the highest-risk periods for iron deficiency, and for a straightforward reason: blood volume expands by roughly 50% to support the placenta and growing baby, and every bit of that expansion needs iron to carry oxygen. The NIH’s Office of Dietary Supplements sets the RDA at 27 mg/day during pregnancy — versus 18 mg/day for a non-pregnant woman of reproductive age, a jump of 50%.
This is exactly why the World Health Organization recommends daily oral iron and folic acid supplementation as a routine part of antenatal care for pregnant women, specifically to reduce the risk of maternal anemia, iron deficiency, and low birth weight — not as an optional add-on, but as a standard part of prenatal protocol in most healthcare settings.
Untreated, iron-deficiency anemia in pregnancy has been associated with a higher risk of preterm delivery and low birth weight, which is part of why ferritin and hemoglobin are checked routinely across antenatal visits rather than just once. The pica connection above is also worth remembering here — unusual cravings during pregnancy are common, but persistent cravings for non-food items are a genuine clinical clue, not just “a pregnancy thing.”
As with every point in this guide, prenatal iron dosing should be confirmed with your own obstetrician or midwife rather than self-selected — pregnancy iron needs vary by trimester and by baseline hemoglobin.
11. Iron Food Sources and What Actually Improves Absorption
Iron comes in two dietary forms: heme iron, found in meat, poultry, and fish, which your body absorbs efficiently, and non-heme iron, found in plant foods, which absorbs considerably less efficiently on its own.
Pairing non-heme iron sources with vitamin C — a squeeze of lemon over leafy greens, or fruit alongside an iron-rich meal — measurably improves how much of that plant-based iron your body actually absorbs. This is the single most useful, zero-cost absorption trick in this entire guide.
Cooking in cast-iron cookware is a small, genuinely effective habit worth knowing, and the numbers are more specific than most people expect: studies on cast-iron cooking found that spaghetti sauce picked up an extra 2–5 mg of iron, chili with meat and beans gained about 5 mg, and applesauce gained roughly 7 mg — with acidic dishes (tomato-based, in particular) picking up meaningfully more than neutral ones, since acidity helps leach iron from the pan into the food itself.


Iron Content by Food
| Food | Approx. Iron | Serving |
|---|---|---|
| Red meat | ~2.5–3 mg | 100g cooked |
| Spinach (cooked) | ~3.5 mg | 1 cup |
| Lentils | ~3.3 mg | 1 cup cooked |
| Chickpeas | ~2.5 mg | 1 cup cooked |
| Jaggery | ~0.5–1 mg | 1 tbsp |
| Fortified cereals | Varies, often 4–8 mg | 1 serving |
The Absorption Blocker Checker
Pick whichever habit sounds most like yours to see the actual spacing rule that fixes it — these apply whether you’re eating iron-rich food or taking a supplement.
12. Before You Start Supplementing
A confirmed deficiency is a genuine reason to supplement. “I read that iron helps with energy” is not — and this is the section most iron-deficiency articles skip entirely, because the overdose story is less appealing than the deficiency story. It’s also the single most important safety point in this guide.
Per the NIH’s own consumer guidance, accidental overdose of iron-containing products is a leading cause of fatal poisoning in children under 6 in the United States. This is not a rare, exotic risk — a 1990s CDC investigation documented five toddler deaths in Los Angeles County alone within an eight-month span from iron supplement ingestion, on top of three earlier deaths in the same county across the preceding years. Iron tablets are small, sometimes sugar-coated, and look like candy to a curious child.
If you keep iron supplements at home, they belong in a child-resistant container, out of sight and out of reach — the same way you’d store any medication that can be fatal in a small overdose, because this one genuinely can be.
For adults, the NIH’s Office of Dietary Supplements sets the Tolerable Upper Intake Level (UL) for iron at 45 mg/day from all sources combined — supplements plus fortified food plus diet. Going meaningfully over this, especially for extended periods without a confirmed deficiency, can cause stomach upset, constipation, nausea, abdominal pain, and vomiting at lower excess levels, and organ damage at much higher, sustained excess. Unlike some nutrients, the body has no efficient way to actively excrete surplus iron once absorbed — it accumulates in organs like the liver and heart over years, which is the same underlying mechanism behind hereditary hemochromatosis, a genetic iron-overload condition. Anyone with a family history of hemochromatosis should be tested before supplementing, not after.
Drug interactions worth knowing before you supplement
Iron is a small, chemically reactive mineral, which means it binds to more medications than most people expect. Three interactions are common enough to name specifically:
- Levothyroxine (thyroid medicine): iron chemically binds to levothyroxine in the gut and blocks its absorption. The standard fix is a 4-hour spacing rule between the two — take them at opposite ends of the day rather than together.
- Certain antibiotics (fluoroquinolones like ciprofloxacin, and tetracyclines): iron chelates with these antibiotics the same way it does with levothyroxine, which can meaningfully reduce how much of the antibiotic your body actually absorbs. The standard spacing is to take the antibiotic 2–4 hours before iron, or wait 4–6 hours after iron before taking the antibiotic.
- Long-term antacids or PPIs: as covered above in the risk-factors section, these reduce iron absorption from food and supplements alike by suppressing the stomach acid iron needs to be converted into an absorbable form — worth reading alongside our chronic antacids guide if you’re on both a PPI and an iron supplement.
None of this is a reason to avoid iron when you genuinely need it — it’s a reason to take it correctly, and to check what else you’re taking before you add it. This is exactly the kind of cross-check our Integrative Interaction Checker is built for.
Iron is always safe because it’s “just a vitamin” you can buy over the counter.
It’s a leading cause of fatal accidental poisoning in young children, and adults have a defined upper limit (45 mg/day) precisely because the body can’t easily get rid of excess.
Actually taking it, once you’ve confirmed you need it
For a confirmed deficiency, supplements are commonly prescribed as ferrous sulfate, ferrous gluconate, or ferric citrate. Taking iron on an empty stomach improves absorption but can cause stomach upset for some people, which is a common reason people stop taking it before finishing a course — taking it with a small amount of food (not dairy or a big meal) is a reasonable compromise if empty-stomach dosing isn’t tolerated.
Constipation and darkened stools are common, generally harmless side effects of oral iron — worth knowing in advance so they don’t cause unnecessary alarm partway through treatment.
Retesting after a few months of treatment, rather than stopping as soon as symptoms feel better, confirms whether ferritin has actually been rebuilt to a healthy reserve level — since feeling better and having fully corrected iron stores aren’t quite the same thing, per the 3-stage model covered earlier.
13. Quick Knowledge Check
Four questions to confirm the mechanisms above actually stuck — not a graded exam, just a gut check.
14. Frequently Asked Questions
What is the earliest sign of iron deficiency anemia?
Persistent fatigue is usually the earliest and most common sign, though it’s also the easiest to dismiss since it overlaps with so many other causes. In terms of lab markers rather than symptoms, ferritin is what actually moves first, in Stage 1, before any symptom shows up at all.
What is Pica and why does it happen with iron deficiency?
Pica is an unusual craving for non-food substances like ice, dirt, or starch. Its exact mechanism isn’t fully understood, but it’s specifically and repeatedly linked to iron deficiency, and cravings often resolve once iron levels are corrected.
What’s the difference between hemoglobin and ferritin tests?
Hemoglobin measures the oxygen-carrying protein currently circulating in your blood (a Stage 3 marker), while ferritin measures your body’s stored iron reserves (a Stage 1 marker). Ferritin typically drops before hemoglobin does, making it a more sensitive early indicator.
How can I tell iron deficiency anemia apart from B12 deficiency anemia?
MCV, a measure of red blood cell size, is the key differentiator. Iron deficiency typically produces smaller red blood cells (low MCV), while B12 deficiency produces larger ones (high MCV).
Why do women need more iron than men?
Menstrual blood loss means women of reproductive age lose meaningful iron every month, which is why the NIH sets their RDA at 18 mg/day versus 8 mg/day for men — more than double.
Should I take iron supplements with tea or coffee?
No. Compounds in tea and coffee bind to iron and significantly reduce absorption, so it’s better to space them at least an hour or two apart from iron-rich meals or supplements.
How long does it take to correct iron deficiency anemia?
Energy levels often start improving within a few weeks, but fully rebuilding iron stores (moving back through all three stages to a healthy ferritin level) typically takes three to six months of consistent supplementation and dietary support.
Can iron deficiency anemia happen without heavy bleeding?
Yes. Poor dietary intake, malabsorption conditions (including long-term antacid or PPI use), frequent blood donation, and endurance exercise can all cause it independent of any obvious blood loss.
Is it safe to take iron supplements without a doctor’s guidance?
It’s better not to. Iron accumulates in the body if not needed — the NIH sets an adult upper limit of 45 mg/day for exactly this reason — and unsupervised long-term supplementation without a confirmed deficiency carries genuine health risks, including for people with undiagnosed hemochromatosis.
Does exercise make iron deficiency anemia worse?
Regular exercise itself doesn’t cause deficiency in most people, but endurance training specifically increases iron turnover and mild gastrointestinal blood loss, making athletes a genuinely higher-risk group worth monitoring.
Can iron supplements interact with my thyroid medication?
Yes. Iron chemically binds to levothyroxine in the gut and blocks its absorption. The standard fix is a 4-hour gap between the two medications, not taking them together.
Is it true that iron overdose can be fatal, especially in children?
Yes, and this is genuinely underappreciated. Per NIH consumer guidance, accidental overdose of iron-containing products is a leading cause of fatal poisoning in children under 6 in the US. Iron supplements should always be stored in child-resistant packaging, out of reach.
Can iron deficiency cause restless legs even without full-blown anemia?
Yes. Research points to a brain-iron and dopamine-receptor mechanism distinct from blood iron levels, and a management algorithm recommends considering oral iron for restless legs when ferritin is 75 ng/mL or below — a level well above what’s usually flagged as “deficient” on a routine report.
How much extra iron do pregnant women need?
The RDA rises to 27 mg/day during pregnancy, up from 18 mg/day — about 50% more — which is why the World Health Organization recommends routine daily iron and folic acid supplementation as part of standard antenatal care.
The Short Version
Iron deficiency moves through three silent stages before it becomes the anemia a routine blood test catches — ferritin drops first, hemoglobin drops last. Fatigue, pale skin, breathlessness, cold extremities, brittle nails, restless legs, and pica are the 7 signs worth watching, and restless legs specifically can show up from a brain-iron mechanism even without anemia. Testing beats guessing either way: a confirmed deficiency is worth fixing properly, but supplementing without one carries a real overdose risk that includes drug interactions with thyroid medicine and certain antibiotics, and — the point this guide leads with — a genuine, well-documented poisoning danger to young children if tablets aren’t stored safely.
Why Trust This Guide
More From the Deficiency Series
- Magnesium Deficiency Symptoms — 8 signs
- Vitamin D Deficiency in India — 7 signs
- Hair Fall Vitamin Deficiency — 5 warning signs
- Protein Deficiency in India — 5 myths busted
- High Uric Acid Diet
- Zinc Deficiency Symptoms — 7 warning signs
- Which Nutrient Deficiency Do You Have? — free 10-nutrient finder tool
- Integrative Interaction Checker — before you supplement
- National Institutes of Health, Office of Dietary Supplements. Iron: Fact Sheet for Consumers. RDA, upper limit (45 mg/day adults), heme/non-heme absorption, and the poisoning-risk statement for children under 6.
- Centers for Disease Control and Prevention. Toddler Deaths Resulting from Ingestion of Iron Supplements — Los Angeles, 1992–1993. MMWR.
- Silber MH, Buchfuhrer MJ, Earley CJ, et al. The Management of Restless Legs Syndrome: An Updated Algorithm. Mayo Clinic Proceedings. 2021 — serum ferritin ≤75 ng/mL threshold and brain iron-dopamine mechanism.
- World Health Organization. Guideline: Daily Iron and Folic Acid Supplementation in Pregnant Women.
- GoodRx Health. Is My Thyroid Medication Working? These Drugs Can Cause Interactions — the 4-hour iron/levothyroxine spacing rule.
- Drugs.com. Ciprofloxacin and Ferrous Sulfate Drug Interaction — chelation mechanism and 2–4hr/4–6hr spacing rule.
- Food Network Healthy Eats. How Much Iron Do I Get From a Cast-Iron Skillet? — iron pickup figures for spaghetti sauce, chili, and applesauce.