For official clinical guidelines and reference data, you can cross-verify resources from the National Kidney Foundation.
 SehatSphere.com
Beyond the Lab Sheet: Why High Creatinine Doesn’t Always Mean Kidney Failure
It was nearly midnight when a 26-year-old walked in clutching a lab printout like it was a legal indictment, one line circled in pen: Serum Creatinine: 1.4 mg/dL, against a reference ceiling of 1.2. “Am I going on dialysis?” he asked. “I work out every day. How did my kidneys fail?” They hadn’t. A single creatinine number, on its own, was never built to answer that question.

Key takeaways:
- Creatinine production depends heavily on muscle mass — the same number means something completely different in a muscular 28-year-old versus a frail 70-year-old.
- India’s chronic kidney disease rate has genuinely risen — from about 11% (2011-2017) to over 16% (2018-2023) in pooled community studies — but a single elevated creatinine still isn’t a diagnosis on its own.
- Certain medications, including one common acid-reflux drug, chemically block creatinine’s normal exit route without touching your actual kidney function at all.
- Real kidney disease has physical warning signs — a lab number by itself usually doesn’t.
Why a Single Number Is Flawed
Creatinine is just a waste byproduct of ordinary muscle breakdown, cleared out by your kidneys’ filtering units at a fairly steady rate. That’s exactly the problem with judging kidney health from it alone: creatinine production is never constant. It moves with how much muscle you carry, what you ate, whether you took a supplement, and how hydrated you are right now — none of which have anything to do with how well your kidneys are actually filtering.
This is why modern nephrology never diagnoses kidney disease from creatinine alone. Your creatinine gets run through an equation alongside age, sex, and sometimes weight to estimate your real filtration rate — the eGFR — which is the number that actually matters. Two people can share an identical raw creatinine and have genuinely different kidneys underneath it, simply because the equation accounts for how much muscle mass was likely producing that number in the first place.
Two Real Patients, Opposite Stories
Nothing makes the muscle-mass problem clearer than putting two real patients side by side, tested on the exact same day with the exact same lab equipment.
A 28-year-old heavy weightlifter, regular creatine and whey user, showed a serum creatinine of 1.5 mg/dL — technically “high.” His actual eGFR, run properly, came back over 105 mL/min. Completely normal. His muscle mass alone explained the number.
A 70-year-old woman with very little muscle mass had a “perfect-looking” creatinine of 0.9 mg/dL. Her actual filtration rate, once calculated properly, put her at Stage 3 chronic kidney disease. Raw creatinine completely missed it — her low muscle mass was quietly hiding a real problem.
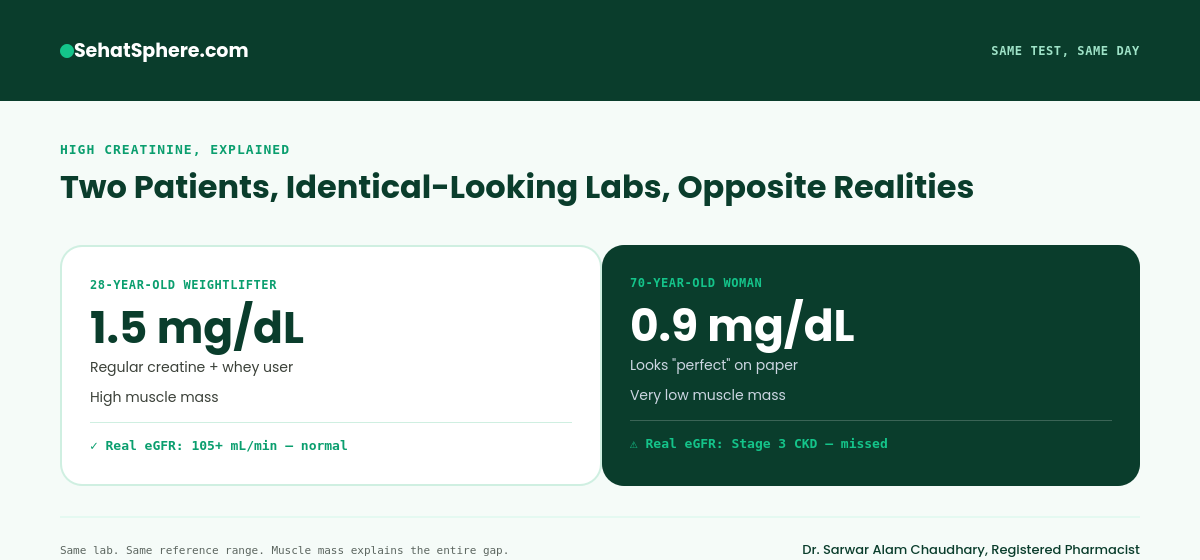
Same test. Same lab. Two people who needed opposite reactions. If you’re someone who takes creatine regularly, our full guide on creatine and your blood test goes deeper into exactly this mechanism — and why the fix usually isn’t stopping the supplement, it’s asking for the right test.
How Common Is This in India?
A 2025 pooled analysis of community-based Indian studies put chronic kidney disease prevalence at 13.24% overall — and the trend is genuinely moving in the wrong direction, rising from about 11.12% in studies from 2011–2017 to 16.38% in studies from 2018–2023. Rural areas ran higher (15.34%) than urban ones (10.65%), and men ran slightly higher than women (14.80% vs 13.51%).
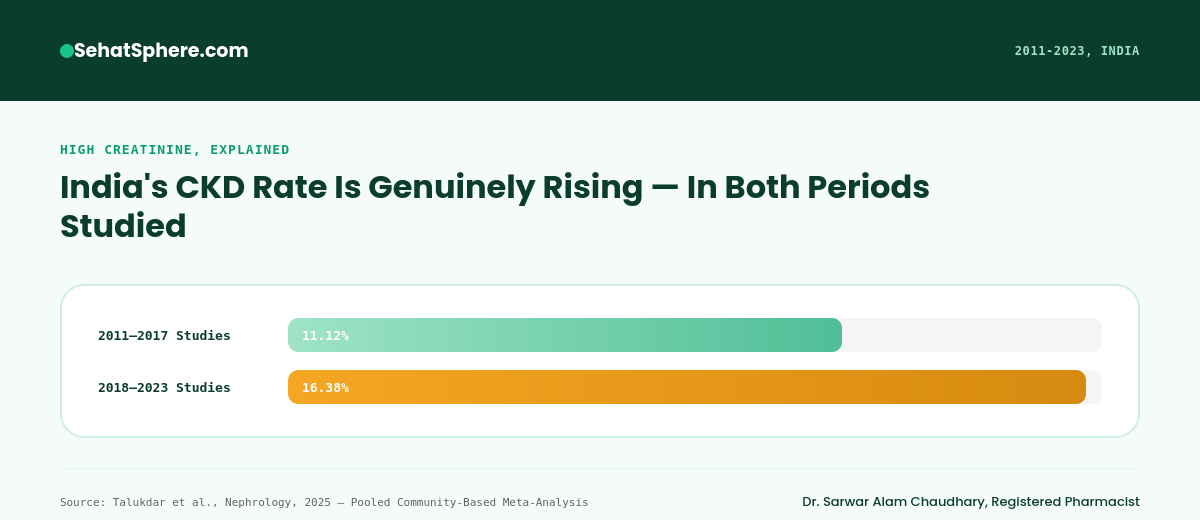
That’s real, and worth taking seriously — but it’s exactly why the muscle-mass problem above matters so much. A rising CKD rate makes it tempting to treat every elevated creatinine as confirmation. The two cases above show why that instinct, applied without context, gets it backwards as often as it gets it right. Diabetes and high blood pressure remain the two biggest drivers of genuine kidney decline worldwide — if either applies to you, our insulin resistance guide and normal blood pressure by age guide are worth reading as prevention, not just reaction. Even ordinary anger and stress genuinely move blood pressure in ways that compound kidney strain over years — something our anger and blood pressure guide covers with the actual research behind it.
What To Read Next
- Creatine and Your Blood Test: Why a supplement can fake this exact same lab flag.
- Free eGFR & CrCl Calculator: Get your real filtration number, not just the raw creatinine.
- Blood Report Decoder: Understand every value on your full metabolic panel.
Medications That Fake the Number
Beyond muscle mass, a specific and genuinely under-discussed category exists: drugs that block creatinine’s exit route in the kidney tubules without affecting real filtration at all — a phenomenon nephrologists call pseudoelevation.
| Medication | Common Use | What It Actually Does |
|---|---|---|
| Cimetidine | Acid reflux, heartburn | Blocks tubular creatinine secretion — raises the number, not the risk |
| Trimethoprim (in Bactrim) | UTI, skin infections | Same mechanism, well-documented in transplant patients |
| NSAIDs (ibuprofen, diclofenac) | Pain, inflammation | Genuinely different — constricts blood flow into the kidney itself |
The NSAID entry is worth pausing on, because it’s a real mechanism, not a false flag like the other two — regular, unmonitored NSAID use is one of the more preventable causes of actual kidney stress, especially when combined with dehydration or existing kidney strain. If you’re also managing acid reflux, our pantoprazole guide and GERD and silent reflux guide cover the other medications in that same cabinet worth mentioning to whoever ordered your kidney panel.
What the eGFR Calculator Actually Does
The current standard formula, CKD-EPI 2021, takes your creatinine, age, and sex and outputs a filtration rate in mL/min — a genuinely different number from the raw creatinine, and the one that actually maps to the five official CKD stages. A 28-year-old and a 70-year-old with the identical creatinine value will get meaningfully different eGFR results, because the formula already knows that muscle mass and filtration both naturally decline with age. This is precisely why running your own numbers through a proper calculator tells you something a lab printout’s bare reference range never can.
The Three Tests, Compared
| Test | What It’s Good For | Its Blind Spot |
|---|---|---|
| Serum Creatinine | Quick baseline screening | Skewed heavily by age, sex, and muscle mass |
| eGFR (CKD-EPI 2021) | Staging real kidney disease | Needs a stable creatinine to begin with |
| Creatinine Clearance | Precise medication dosing | Needs an accurate body weight to calculate |
Normal serum creatinine itself runs roughly 0.7–1.3 mg/dL for men and 0.6–1.1 mg/dL for women — the gap exists purely because of average muscle mass differences, not because women’s kidneys work differently. Severe kidney impairment is generally associated with levels reaching 5.0+ in adults, a very different picture from a borderline 1.4. If you’re on multiple long-term prescriptions — cholesterol medication being one of the most common — periodic kidney monitoring becomes more relevant simply because more drugs are being cleared through the same filtering system. Our statins guide covers this from the cholesterol-medication side specifically.
Other Supplements Worth a Second Look
Creatine isn’t the only supplement people take that quietly interacts with this picture. Taurine, increasingly popular in energy drinks and stacks, and apple cider vinegar, often taken on faith for “detox,” both deserve the same scrutiny — our taurine guide and ACV guide cover what’s actually established versus marketed. If your daily “proffee” habit is part of your routine, our proffee guide is worth a look too, since caffeine and protein together can layer small effects on top of each other.
None of this means cutting these out reflexively. It means knowing what you’re actually taking before a lab result surprises you — and if cost is part of why you’ve been substituting supplements for prescribed medication, our guide to generic medicine pricing is worth reading before making that trade-off.
What to Eat While You Figure It Out
The instinct after seeing a high number is often drastic dieting or fasting — not usually the right move before you know why the number is high in the first place.
| Lean Into | Go Easy On |
|---|---|
| Steady hydration (per your own thirst, not forced) | Heavy protein powders and high-dose creatine, until you know the cause |
| Moderate high-quality protein (eggs, poultry) over heavy red meat | Excess sodium and processed food |
| Fresh, low-potassium produce | Unmonitored “kidney cleanse” herbal products |
If mineral absorption is already a concern for other reasons, our guide on chronic antacids and mineral malabsorption and magnesium and your medications are worth reading alongside this one, since several of the same medications show up in both conversations. Fatigue specifically gets blamed on kidneys often when the real cause is a separate nutrient gap — our B12 deficiency guide and the free Nutrient Deficiency Symptom Finder are worth ruling out before assuming it’s renal.

If your medication list is genuinely long, running it through our free Integrative Interaction Checker takes a couple of minutes and flags exactly this kind of overlap.
The Real Warning Signs
Persistent swelling in the ankles, lower legs, or around the eyes; urine that consistently looks foamy or bubbly (a sign of protein leaking through); unexplained fatigue, nausea, or loss of appetite; and blood pressure that suddenly becomes hard to control despite your usual medication. These are physical signs a lab number alone can’t fake — if any of these show up alongside a high creatinine, that combination deserves a doctor’s attention, not a home remedy.
If your blood pressure specifically is part of this picture, our Complete Guide to Blood Pressure and BP fluctuation guide cover the kidney-BP relationship in more depth, since the two genuinely affect each other in both directions.
Quick Self-Check
Tick anything that applies to you, and see what it suggests.
Frequently Asked Questions
Can dehydration make creatinine look like kidney failure?
Yes. When you’re low on fluids, plasma volume drops and waste products like creatinine concentrate, registering artificially high. Proper rehydration often brings the number back down within days.
Do medications really affect kidney lab results?
Yes, in two genuinely different ways. NSAIDs can cause real, if usually temporary, reduced blood flow into the kidney. Drugs like cimetidine and trimethoprim block creatinine’s exit route without touching actual filtration – a false flag, not real damage.
How does chronic kidney disease progress through its stages?
CKD is staged 1 through 5 based on eGFR. Stages 1-2 involve mild changes manageable through blood pressure and blood sugar control. Stages 3-4 require careful medication dose adjustments. Stage 5 is end-stage disease requiring dialysis or transplant.
Do bodybuilding supplements affect kidney test results?
Yes – creatine supplements increase the waste byproduct measured on the test, which can push a calculated eGFR down even when real kidney function hasn’t changed.
What should I eat if my creatinine is high?
Moderate high-quality protein, steady hydration, fresh low-potassium produce, and reduced sodium – while you and your doctor work out why the number is elevated in the first place.
How common is chronic kidney disease in India?
A 2025 pooled analysis found 13.24% prevalence in community studies, rising from about 11% (2011-2017) to over 16% (2018-2023) – a genuine upward trend worth taking seriously.
What’s a normal creatinine range?
Roughly 0.7-1.3 mg/dL for men and 0.6-1.1 mg/dL for women, with the difference reflecting average muscle mass rather than different kidney function between sexes.
When is a high creatinine actually an emergency?
When it comes with physical symptoms – persistent swelling, foamy urine, unexplained fatigue or nausea, or blood pressure that suddenly won’t respond to your usual medication. The number alone, without symptoms, rarely is.
The Bottom Line
A high creatinine is an invitation to ask “why,” not a verdict on your kidneys. Muscle mass, hydration, diet, and a specific short list of medications can all move this one number without your kidneys changing at all – which is exactly why nephrology never reads it alone. The eGFR calculated from it, your actual symptoms, and a conversation with your doctor are what turn a scary-looking lab line into an actual answer. If you take nothing else from this guide, take this: the number on the page is a starting question, and the calculator, the symptom check, and the doctor’s conversation are what actually answer it.
- Talukdar A, et al. Chronic Kidney Disease Prevalence in India: A Systematic Review and Meta-Analysis, 2011-2023. Nephrology, 2025.
- National Kidney Foundation. Creatinine. kidney.org
- MDTools. Creatinine Levels – Normal Range by Age. mdtools.org
View All References (5) ▾
- GoodRx Health. High Creatinine Levels: Medications and Other Causes. goodrx.com
- Mayo Clinic. Creatinine Test. mayoclinic.org